An Unusual Case of Allograft Nephromegaly Secondary to Renal Lymphangiectasia Presenting Several Years Following Deceased Donor Kidney Transplantation
Introduction: Renal lymphangiectasia is a rare condition characterized by nephromegaly secondary to benign intrarenal or extrarenal lymphatic dilatation with perinephric leakage. Only a few isolated case reports exist following kidney transplantation (KT).
Methods: We report herein a case of allograft nephromegaly occurring several years following deceased donor kidney transplantation.
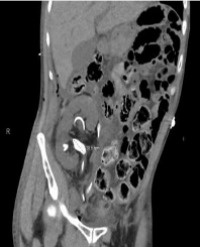
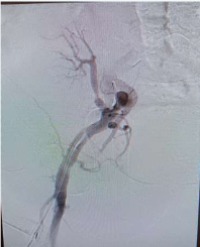
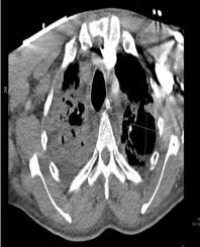
Results: The patient underwent KT in 2009 and initially did well. In 2017, he noticed fluid retention with lower extremity and abdominal swelling that improved with diuretic therapy and was not associated with proteinuria. He returned in 2023 at which time he had significant weight gain and intermittent leakage of clear fluid from his transplant incision. Computerized tomographic imaging of the abdomen and pelvis revealed ascites, fluid-filled left inguinal and supraumbilical hernias, and allograft enlargement with perinephric fluid. He was again managed medically with diuretic therapy. He eventually presented in 2026 with recurrent allograft nephromegaly, a large perinephric fluid collection with extension into the psoas muscle, and fluid-filled hernias. Multiple imaging modalities and repeated percutaneous drainage procedures as well as attempted lymphatic ablation failed to reveal a specific etiology or completely resolve the above findings. Due to the infiltrative nature of the imaging findings, a kidney biopsy was recommended but the patient refused. Serum creatinine has remained stable in the 1.6 mg/dl range with no significant proteinuria. Symptoms have improved with diuresis and intermittent drainage.
Conclusion: Renal lymphangiectasia is an extremely rare condition that is largely a diagnosis of exclusion. Pathophysiology is unclear although the few cases reported following KT have occurred many years later. Management is primarily medical and expectant although symptomatic patients can be treated with repeated aspiration, drainage, or rarely surgical peritoneal fenestration. Nephrectomy is rarely indicated in the absence of suspected malignancy.
Rana Kumar, Robert Stratta, Erin M. Moore, Alan C. Farney, Giuseppe Orlando, Emily McCracken, Christopher J. Webb, and Robert J. Stratta*